

When intraocular pressure remains above target or fluctuates, the instinct may be to question whether the glaucoma medication is providing enough pressure reduction.
Long-term glaucoma control depends not only on what is prescribed, but on whether treatment can be used consistently: remembering doses, instilling drops correctly, tolerating ocular surface effects, and sustaining the routine.
That creates an important clinical question: is the treatment failing pharmacologically, or has it become too difficult to use reliably?
To understand that distinction, MDForLives surveyed ophthalmologists across six countries. The findings point to a practical journey shaped by adherence, ocular-surface health, regimen burden, and decisions about reducing daily-drop dependence. The detailed findings are available in the MDForLives Glaucoma Eye-Drop Adherence Insight Report.
Check Adherence Before Changing Therapy
An elevated IOP does not explain why pressure is elevated.
The medicine may be insufficient, or disease may be progressing. But doses may also be missed; refills delayed, or drops used inconsistently.
That means adherence should remain part of the differential when pressure control does not match the prescribed glaucoma medical treatment.
Before adding another medicine, clinicians may need to review dosing, refill history, instillation technique, tolerability, and whether the patient can realistically manage the regimen.
Before escalating therapy, confirm that the intended treatment is reaching the eye consistently.
Pressure variability can be an adherence signal, not just a drug-efficacy signal
Because non-adherence is rarely observed directly, clinicians often work from patterns rather than a single measure.
In the MDForLives survey, 45.6% of ophthalmologists selected a significant IOP discrepancy between routine visits and unplanned re-checks as the strongest clue that inconsistent use may be contributing to poor control.
One reading cannot establish adherence. More useful clues include whether pressure fits the prescribed therapy, refills occur as expected, progression matches the IOP pattern, and instillation technique is correct.
Misclassifying an adherence problem as pharmacologic failure can increase treatment burden without correcting the reason.
Ocular-surface discomfort making effective treatment unsustainable
Alongside dosing consistency, tolerability can determine whether treatment works in real life.
Among surveyed ophthalmologists, 36.8% identified ocular surface disease; including burning, hyperemia, or chronic discomfort as the leading single driver of long-term non-adherence.
A glaucoma medication may lower IOP effectively in principle yet become difficult to sustain if glaucoma eye drops cause persistent irritation.
The response should match the barrier. Managing ocular-surface disease, reducing preservative exposure, changing formulation, or reconsidering topical burden may be more useful than reinforcing the same instructions.
If drops are difficult to tolerate, asking for better adherence alone may not solve the problem.
More bottles can make poor control harder to solve
Additional medicines may mean more bottles, schedules, administration errors, and ocular-surface exposure. For patients with dexterity, vision, cognitive, or treatment-fatigue challenges, an effective regimen may become impractical.
This is why the next step in glaucoma treatments is not always another drug.
When tolerability or dosing schedules became difficult, 40.4% of surveyed ophthalmologists said their first adjustment was once daily dosing or a fixed-dose combination.
Fewer treatment actions can reduce the gap between the regimen prescribed and the treatment actually received.
Before intensifying therapy, it may be worth asking whether the regimen can first be made easier to carry out reliably.
When daily drops become the barrier
Simplifying topical therapy will not solve every adherence problem.
Some patients continue to struggle with physical administration, persistent ocular-surface disease, or the burden of daily treatment for years. That is where selective laser trabeculoplasty (SLT) changes the discussion.
In the survey, 40.0% of ophthalmologists reported using SLT as a first-line option before topical therapy, while another 40.0% considered it early when non-adherence or ocular-surface disease became evident.
This does not make SLT a universal replacement for glaucoma eye drops. Suitability still depends on glaucoma type, pressure targets, previous treatment, access, expected response, and individual factors.
When daily self-administration is undermining control, a non-drop approach can enter the conversation earlier.
*When daily glaucoma drops become difficult to sustain, procedural options may become part of the treatment discussion. Explore glaucoma surgery, including its types, risks, and recovery.
The question becomes less about “Which drop should we add?” and more about “Should long-term control depend this heavily on daily drops?”
When Self-Administration Limits Glaucoma Control
Longer-acting delivery approaches can reduce how much of the pressure-lowering effect depends on daily self-administration.
That may be relevant when the barrier is structural dexterity or cognitive limitations, documented adherence difficulty, topical intolerance, or a need for further pressure lowering without more daily drops.
Sustained-release therapy is more than a convenient form of glaucoma medication. Its potential value is greater when reminders or counseling cannot overcome difficulty with self-administration.
The central question remains: which treatment design gives this patient the best chance of receiving the intended pressure-lowering effect consistently?
Closing perspective: sometimes the regimen needs to change, not the patient
Poor glaucoma control does not always mean the prescribed medicine lacks efficacy.
The gap may sit between prescription and delivery: missed doses, difficult technique, ocular-surface discomfort, regimen complexity, or treatment fatigue. These factors can overlap.
That is why glaucoma adherence is increasingly a treatment-design question.
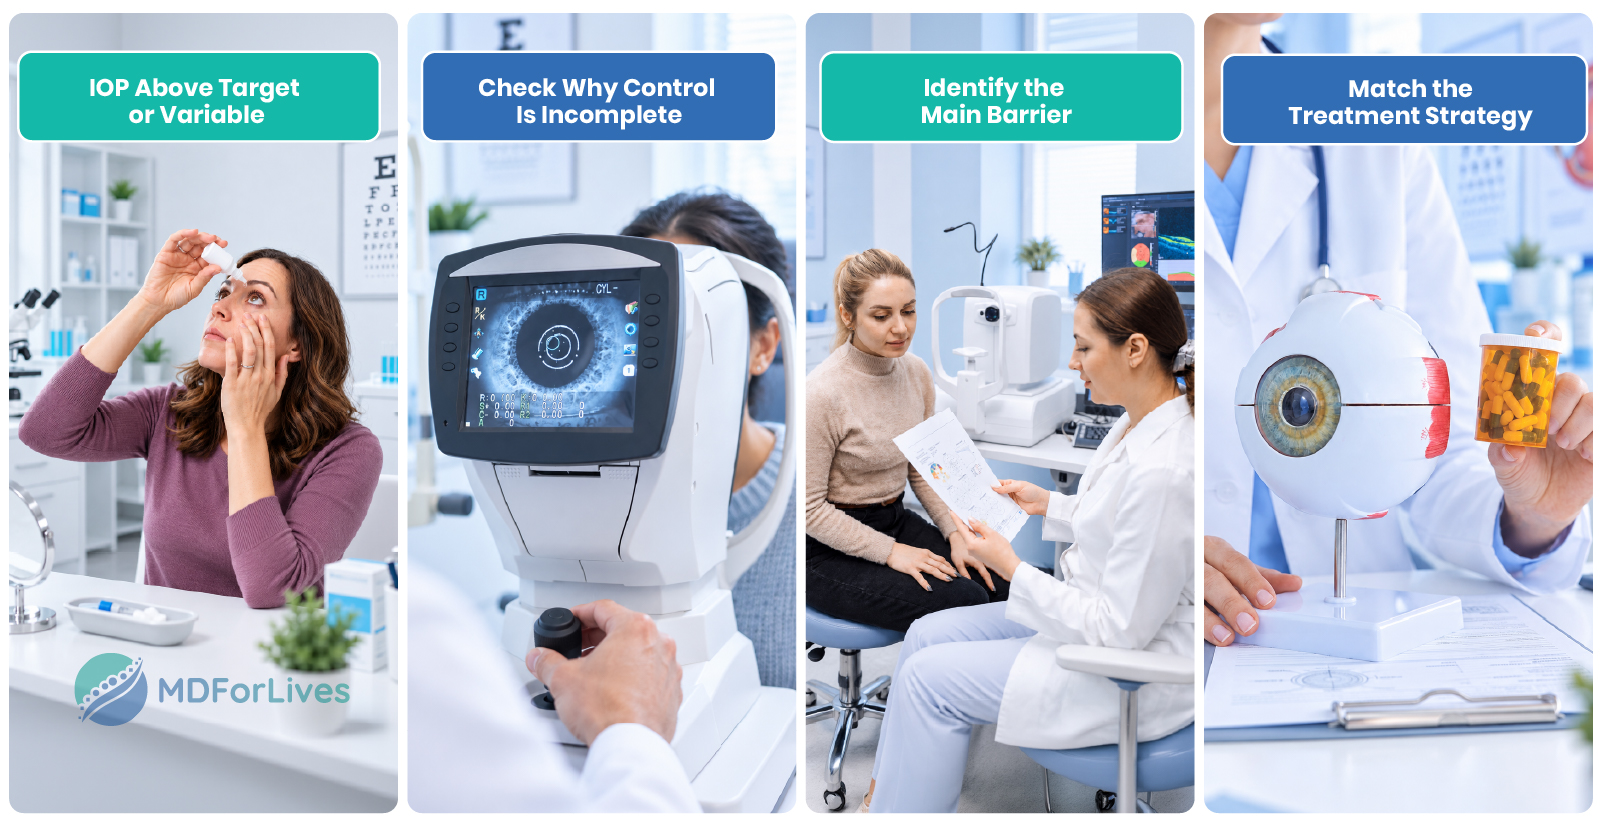
A practical approach is to establish whether treatment is being used consistently, identify the dominant barrier, simplify where possible, protect the ocular surface, and consider reducing dependence on daily drops when burden becomes limiting.
For ophthalmologists, the goal is not to choose between drops and procedures as competing philosophies. It is to match the glaucoma treatment to the barrier most likely to undermine long-term IOP control.
An effective medicine can only deliver its intended benefit when the treatment pathway makes consistent use possible.




