

Normal liver enzymes can feel reassuring. An ALT or AST result within range may appear to lower the likelihood of significant liver disease.
But fatty liver disease does not always follow that pattern.
Metabolic dysfunction-associated steatotic liver disease (MASLD), which replaces the former Nonalcoholic Fatty Liver Disease (NAFLD) terminology, is closely linked to cardiometabolic risk. Obesity, type 2 diabetes, dyslipidemia, hypertension, or multiple metabolic risks may be present without an abnormal liver-enzyme signal.
That creates an important primary-care question: when metabolic risk is visible, but liver enzymes are normal, should assessment stop?
MDForLives surveyed family physicians and general practitioners across six countries to understand how clinicians approach this decision. The findings suggest that many already look beyond liver chemistry toward metabolic risk and structured fibrosis assessment. The detailed findings are available in the MDForLives MASLD in Primary Care Insight Report.
Normal liver enzymes should not automatically close the fatty liver question
Routine liver chemistry is familiar and accessible. Its limitation is that liver-enzyme elevation and fibrosis risk do not always move together.
In the MDForLives survey, 34.7% of clinicians said further assessment was likely despite normal liver enzymes depending on the clinical picture. Another 29.9% said it was very likely when multiple risk factors were present.
The clinical implication is that fatty liver with normal liver enzymes can still warrant risk assessment.
Normal aminotransferases should therefore be interpreted within the broader metabolic picture rather than used as a stand-alone rule-out. When diabetes, obesity, dyslipidemia, hypertension, incidental steatosis, or multiple cardiometabolic risks are present, the more relevant question may be whether liver fibrosis also needs assessment.
Metabolic risk may identify fatty liver disease before liver tests do
Primary care is well placed to recognize MASLD because its major risk factors are already visible during routine chronic disease management.
In the survey, 90.6% of respondents selected obesity, dyslipidemia, or hypertension with metabolic risk as reasons to consider MASLD assessment. Diabetes, prediabetes, and multiple cardiometabolic risk factors were also widely recognized as triggers.
Practical shifts are important. Instead of waiting for abnormal liver chemistry, clinicians can consider whether the patient’s metabolic profile itself warrants further assessment.
This matters because fatty liver disease symptoms may be absent or non-specific. The metabolic story may become visible through diabetes, obesity, lipid, or blood-pressure care before the liver produces an obvious signal.
Fatty liver disease can remain difficult to recognize when symptoms are limited or absent. Explore why MASLD liver disease can be silent and why earlier recognition matters.
How is fatty liver diagnosed when liver enzymes are not enough?
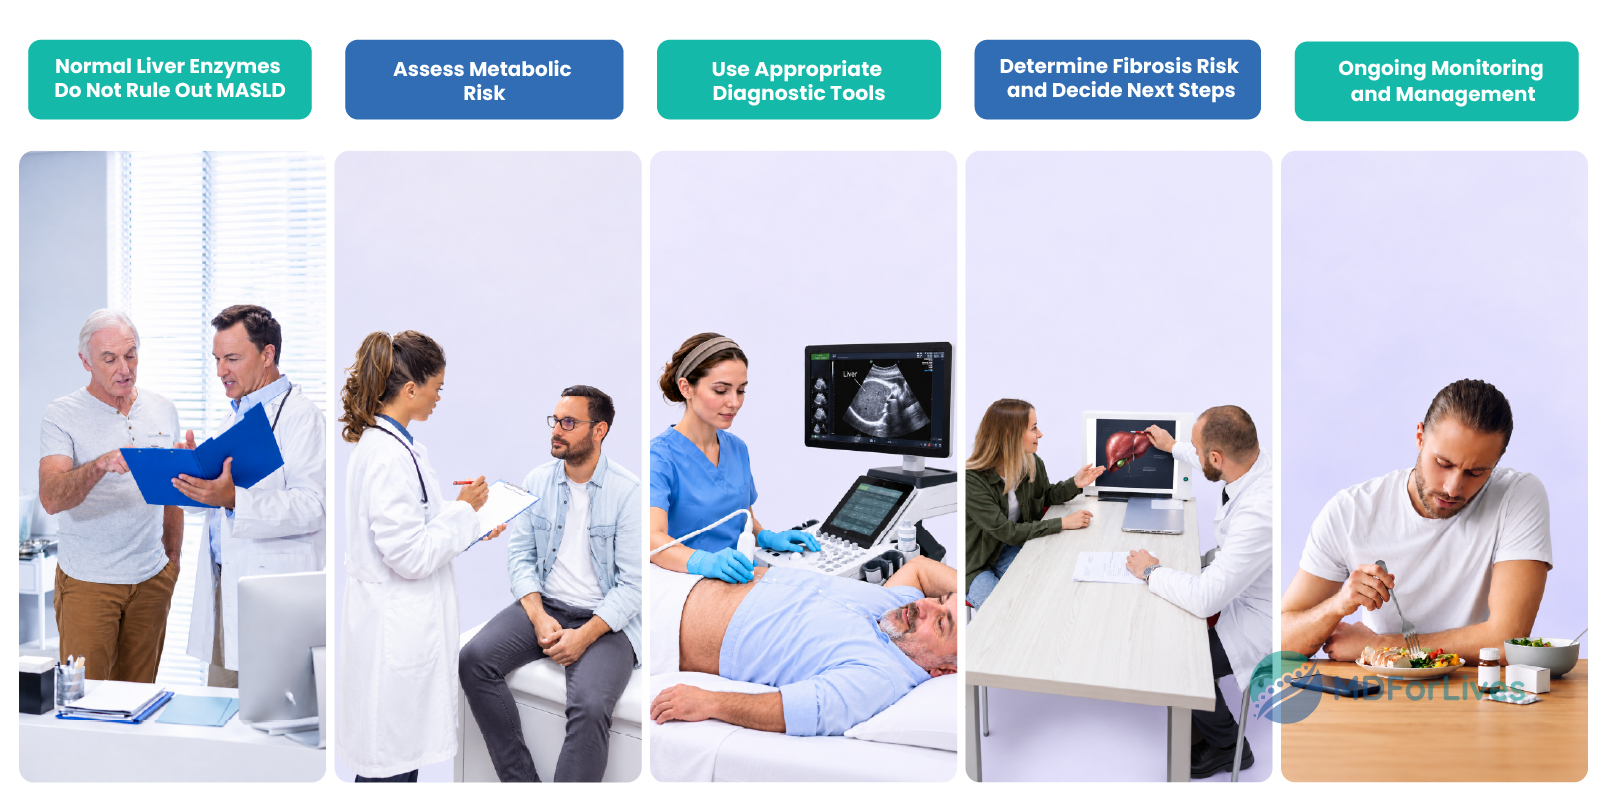
The phrase “fatty liver diagnosis” can imply a single test, but the primary care pathway is more layered.
The first question is whether the patient warrants MASLD assessment. The next is whether steatosis is present and, importantly, whether clinically relevant fibrosis risk needs to be evaluated.
FIB-4 uses age, AST, ALT, and platelet count to support fibrosis risk stratification. Transient elastography, including FibroScan, offers another non-invasive way to assess liver stiffness.
In the survey, 53.1% reported using FIB-4 or another structured fibrosis score, while 56.8% reported using transient elastography, FibroScan, or another elastography approach.
The point is not to choose one test over another. It is to create a clear pathway from metabolic risk to fibrosis risk, rather than allowing normal liver enzymes to end the assessment prematurely.
Liver fibrosis is the finding that changes the clinical pathway
Identifying steatosis matters, but fibrosis risk often determines what happens next.
A lower-risk patient may remain within structured primary care follow-up, while an intermediate, uncertain, or higher risk result may warrant further non-invasive testing, specialist discussion, or referral.
In the survey, 57.9% of clinicians said referral to gastroenterology or hepatology was their usual next step when non-invasive assessment suggested a higher risk of advanced fibrosis.
The value of fibrosis assessment is therefore practical: it helps distinguish who can remain within primary care from who may need further evaluation.
A useful pathway should answer three questions: Who should be assessed? What should follow the first fibrosis risk result? And when should specialist care begin?
A normal result is reassuring only when it answers the right question
A normal ALT or AST answers a biochemical question. It does not necessarily answer the fibrosis question.
A patient with multiple cardiometabolic risk factors may still warrant structured assessment even when routine liver chemistry appears unremarkable.
This does not mean every patient with normal liver enzymes requires elastography or specialist referral. The decision should reflect the overall risk profile and an appropriate stepwise pathway.
For Doctors, the practical shift is from asking only, “Are the liver enzymes abnormal?” to asking “Is this patient’s metabolic risk high enough that fibrosis assessment should still be considered?”
That distinction helps keep the focus on clinically relevant liver risk rather than one reassuring laboratory result.
Testing access can determine whether risk recognition leads to action
Recognizing metabolic risk only helps if the next step is available.
In the MDForLives survey, 56.7% identified limited access to fibrosis testing and diagnostic tools as a barrier. Similarly, 58.4% selected better access to non-invasive fibrosis testing and clinical decision support as a leading opportunity to improve earlier care.
The clinical challenge is therefore not simply awareness. A clinician may recognize risk and perform an initial assessment, but an indeterminate or elevated result needs a clear route to further testing, specialist advice, or referral.
The pathway needs to connect metabolic risk → fibrosis assessment → second-tier testing → referral or follow-up without unnecessary gaps.
Closing perspective: normal liver enzymes do not necessarily mean low liver risk
The issue is not whether liver enzymes are useful. It is whether they are being asked to answer a question they cannot answer alone.
Normal liver chemistry can coexist with meaningful metabolic risk. The MDForLives findings suggest that many family physicians and GPs already look beyond enzymes when the broader clinical picture warrants it.
The opportunity is to make that reasoning more consistent: identify metabolic risk, decide whether MASLD assessment is appropriate, estimate fibrosis risk with non-invasive tools, and make the next testing or referral step clear.
For fatty liver disease, earlier recognition may depend less on waiting for an abnormal liver signal and more on acting on the metabolic signals already visible in routine care.




