
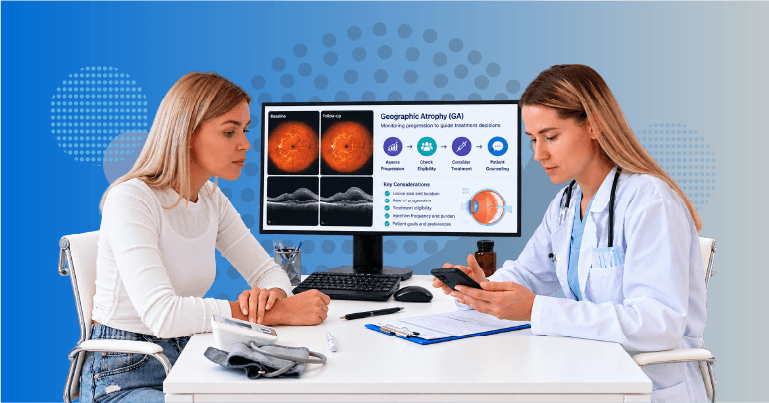
Geographic atrophy is no longer managed only by watching and waiting.
For years, the hardest part of GA care was explaining progression without having an approved therapy to offer. Today, the conversation has changed. Ophthalmologists can discuss active treatment. Patients can ask whether intervention is appropriate. Imaging can show progression patterns. Retina care has moved from observation toward selective intervention.
But that shift has not made decisions simpler.
The MDForLives survey data shows a clear tension: 52.0% of ophthalmologists manage GA patients weekly, yet 40.0% identify choosing the right patient and timing as the biggest hesitation in treatment decisions.
That is the new challenge in geographic atrophy treatment. The question is no longer only whether treatment exists. It is whom to treat, when to begin, and how to explain benefit when the goal is slowing progression rather than restoring lost vision.
GA Has Become Routine Retina Care
The first signal is frequency. More than 90% of clinicians in the MDForLives survey data manage GA at least monthly, with 52.0% doing so weekly.
That makes geographic atrophy a consistent part of ophthalmology practice, not a rare late-stage discussion. Increased detection, greater use of imaging, patient awareness, and the availability of treatment options have all moved GA into more active clinical conversations.
This matters because routine exposure increases pressure for routine decision-making. When a disease is encountered frequently, clinicians need more than awareness. They need repeatable pathways for imaging assessment, risk evaluation, patient counseling, follow-up, and treatment selection.
In GA, those pathways are still taking shape.
Treatment Conversations Are Moving Earlier
The survey data shows that 44.0% of ophthalmologists report treatment conversations happening earlier in the disease course. Another 28.0% note a greater focus on progression risk and earlier intervention.
This is one of the most important shifts in GA management.
Earlier conversations do not always mean earlier injections. They mean patients are being introduced sooner to the possibility of treatment, the nature of progression, and the need to monitor lesion change over time.
This earlier engagement is clinically meaningful because GA can affect daily function even before central vision is completely lost. Reading, low-light adaptation, facial recognition, and driving confidence can all become part of the discussion.
Still, earlier discussion has created a new responsibility: explaining geographic atrophy treatment before the patient may feel urgent functional loss.
The Core Gap Is Patient Selection and Timing
The central barrier is not disease recognition. It is action clarity.
In the MDForLives survey data, 40.0% identify choosing the right patient and timing as the greatest hesitation in GA treatment decisions. This is the practical heart of retina care today.
Ophthalmologists are weighing lesion location, growth pattern, foveal proximity, fellow-eye status, functional impact, visual dependence, and patient willingness to accept long-term visits and injections. None of these factors can be reduced to a single rule.
That is why geographic atrophy treatment remains highly individualized.
Treatment availability has advanced faster than standardized confidence around initiation. Clinicians are not simply asking, “Can we treat?” They are asking, “Will treatment make enough meaningful difference for this patient, at this point, with this burden?”
Treatment Decisions Are Risk-Driven
Without fully standardized real-world pathways, ophthalmologists appear to rely heavily on risk signals.
The survey data shows that 44.0% base treatment discussions on progression risk and lesion characteristics, while 28.0% consider risk to the better-seeing eye.
This makes clinical sense. GA treatment decisions are often most compelling when risk feels visible: lesion progression is meaningful, central involvement is approaching, the fellow eye carries high functional importance, or the patient is beginning to experience daily-life impact.
But risk-driven care can also mean treatment discussions become reactive. Action may wait until progression becomes clinically obvious rather than beginning at the earliest confirmed diagnosis.
That caution reflects clinical realism. It also shows why better patient selection tools and stronger real-world outcomes data matter.
Burden Is Not a Side Issue. It Is Central to the Decision
The strongest barrier to broader use is treatment burden. In the survey data, 44.0% cite treatment burden and visit frequency as the biggest barrier to broader GA treatment use. Another 36.0% point to uncertainty around real-world functional benefit.
These two concerns belong together.
If a therapy requires repeated intravitreal injections and sustained monitoring, the expected benefit must feel clear enough to justify the burden. This is especially important because current GA therapies are designed to slow lesion growth, not restore lost vision.
For clinicians, the burden-benefit conversation is not abstract. It includes patient age, mobility, caregiver support, injection tolerance, access, cost, follow-up reliability, bilateral disease, and expectations.
Geographic atrophy treatment is therefore not only a retina decision. It is a long-term adherence decision.
Counseling May Be the Hardest Part
The survey data shows that 48.0% identify explaining that treatment slows progression rather than restores vision as the greatest challenge in counseling patients.
That is a critical insight.
Patients often understand treatment through the language of improvement. In wet AMD, many patients have heard that injections may stabilize or improve vision. In GA, the conversation is different. The goal is to slow decline, preserve remaining function for longer, and reduce the pace of anatomic progression.
This is harder to communicate because success may feel invisible. A patient may not “feel better” after treatment. The benefit may be measured in slower worsening, not immediate improvement.
That makes expectation-setting central to geographic atrophy treatment. If the goal is misunderstood, persistence may suffer.
Adoption Is Real, but Still Selective
The survey data shows that 44.0% say GA therapy has meaningfully changed management in selected patients, while 40.0% say it remains highly selective in real-world use.
This is the most balanced summary of current practice.
GA therapy is not being ignored. It is influencing conversations and changing care for some patients. But it has not become a broad default. Ophthalmologists are using it carefully, often where risk, patient understanding, and treatment feasibility align.
That selectivity is not necessarily a failure. It may be the natural early phase of real-world adoption when clinicians are still learning which patients derive the clearest practical value.
What Will Change the Next Phase?
Looking ahead, ophthalmologists in the MDForLives survey data are clear about what could shift practice. Nearly 48.0% believe new therapies with a better burden-benefit balance will drive change, while 28.0% call for stronger real-world persistence and outcomes data.
This points to the next stage of GA care.
The field does not only need more treatment availability. It needs better clarity on patient selection, more practical treatment pathways, stronger evidence on persistence, improved imaging and progression assessment, and therapies that reduce burden while preserving meaningful benefit.
Until then, geographic atrophy treatment will continue to be available, discussed, and used, but selectively.
Closing Perspective
Geographic atrophy care has changed.
Treatment conversations are earlier. Imaging is more central. Patients are more aware. Ophthalmologists are weighing active intervention where observation once dominated.
But the MDForLives findings show that action remains cautious. Patient selection, treatment timing, injection burden, functional benefit, counseling, and long-term persistence still shape real-world decisions.
The challenge is no longer whether GA can be treated.
The challenge is whether treatment fit is clear enough to act with confidence.
For retina care, that may be the defining question of the next few years: not simply how to slow progression, but how to choose the right patient, at the right time, with the right expectation.




