

Initiating a GLP-1 receptor agonist can feel like the decisive step in obesity management, but the prescription is only the starting point. The more difficult question is whether therapy remains affordable, tolerable, understandable, and practical enough to continue month after month. In other words, GLP-1 medication adherence, not initiation, increasingly determines whether the clinical benefit is sustained.
Obesity is increasingly managed as a chronic disease. WHO guidance frames GLP-1 therapies as a possible long-term option within comprehensive obesity care, and the American Diabetes Association’s Standards of Care recommend continuing chronic obesity pharmacotherapy beyond a weight-loss target when it remains clinically appropriate. Against that backdrop, GLP-1 medication adherence shapes whether treatment benefits are maintained over time.
To understand where therapy breaks down, MDForLives surveyed endocrinology and diabetes specialists across six countries. The full findings are available in the MDForLives GLP-1 Persistence in Obesity Insight Report. The survey points to a practical adherence story shaped by access, tolerability, expectations, titration, and follow-up.
Affordability can end adherence before pharmacology does
Asked to identify the single most frequent reason patients stop GLP-1 therapy early, 63.0% of clinicians selected high out-of-pocket cost or lack of insurance reimbursement.
The deeper message is that persistence can fail before pharmacology does: an effective therapy is still difficult to sustain when cost, reimbursement, formulary restrictions, authorization requirements, or availability change. For practice, that places affordability, and a contingency plan if access changes, in the first consultation, where it can matter to adherence as much as counseling on administration. Once the cost is settled, tolerability is the next test.
Difficult early tolerability calls for adaptation, not abandonment
Nausea, vomiting, constipation, and diarrhea are recognized GI adverse effects of GLP-1 therapy, most often during initiation or dose titration, and the survey indicates that clinicians typically manage tolerability rather than discontinue at the first difficulty. When adverse effects or a weight plateau became challenging, 51.9% reported that their most common next step was to reduce the dose to the last tolerated level and pause titration.
The clinical signal is that early tolerability problems usually call for adaptation rather than immediate treatment abandonment, consistent with ADA guidance on gradual, individualized titration. Patients should not self-adjust doses, but requiring more time at a lower dose does not signify failure, an important message during the vulnerable early weeks. When tolerability is manageable, expectations become the next variable to address.
An expectation gap can become an adherence gap
Clinicians repeatedly pointed to three expectations that can undermine persistence: rapid, dramatic loss in the first weeks; the belief that medication removes the need for diet and exercise; and the assumption that weight loss persists after stopping.
In clinicians’ view, patients disengage when progress feels slow, when a plateau reads as failure, or when they assumed therapy was temporary, so an expectation gap can quietly become an adherence gap. Calibrating expectations before initiation, covering the likely pace of response, the continued role of nutrition and physical activity, anticipated GI adverse effects, the titration schedule, planned follow-up, and the possibility that obesity pharmacotherapy may be long term, is one of the clearest ways to protect GLP-1 medication adherence. That preparation connects directly to how titration is planned.
Personalized titration and counseling are set up before the first dose
Perhaps the most actionable finding is what clinicians believe prevents drop-off. Slower, personalized dose titration and comprehensive pre-treatment counseling are tied as the leading strategies for improving one-year persistence, each selected by 40.7%.
The unifying principle is preparation: one lever makes titration more adaptable, and the other reduces surprise by clarifying what therapy can and cannot achieve. Because both are set up before treatment begins, the strongest opportunity to protect GLP-1 medication adherence arises before frustration develops, not after a patient has already disengaged.
Match multidisciplinary support to the individual patient
Clinicians were divided on the intensity of structured support required. Some viewed multidisciplinary support as critical, others saw it as most useful for selected high-risk patients, while some considered focused physician follow-up sufficient for most.
This favors flexible, stratified support over a single universal program. Some patients benefit from dietitians, pharmacists, nurses, or behavioral-health input when cost, adverse effects, expectations, or adherence become difficult; others do well with focused clinician follow-up. The task is matching support to the individual patient, and planning in advance for what should happen if treatment is later stopped.
Plan the exit: weight regain can follow withdrawal
Because obesity is chronic, the end of a treatment course deserves as much planning as the start. Current guidance treats obesity pharmacotherapy as long-term treatment while it remains effective, tolerable, and appropriate, and the evidence shows weight regain can follow withdrawal. In the STEP 1 trial extension, participants who stopped semaglutide 2.4 mg after 68 weeks regained roughly two-thirds of their lost weight over the following year. That reflects one agent in a defined trial population, so it is not an exact prediction for every patient, but it supports agreeing with a monitoring and maintenance plan with the patient rather than an abrupt stop. Anticipating that conversation early is itself part of protecting long-term adherence.
Closing perspective: designing for adherence
The question behind GLP-1 treatment drop-off is not simply why a patient stopped; the more useful clinical question is what made continuation difficult, and whether it could have been anticipated.
The findings describe an accumulation of friction. Cost can render therapy unreachable, GI adverse effects can complicate titration, unrealistic expectations can make normal progress feel like failure, and limited support can leave key decisions unresolved. Any single factor can quietly interrupt treatment.
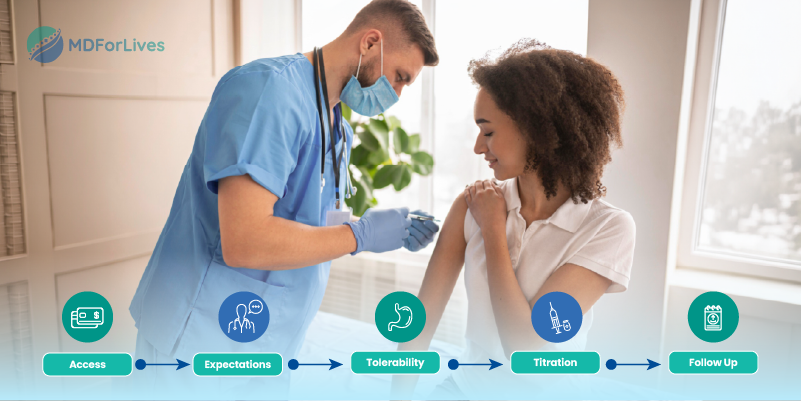
That is why GLP-1 medication adherence may begin before the first dose. When access, expectations, tolerability, titration, and follow-up are addressed early, and the eventual question of stopping is planned rather than improvised, adherence becomes part of treatment design rather than a problem identified after therapy has already been interrupted.
For a broader perspective on how access barriers and continuation challenges can affect long-term GLP-1 use in obesity care, read GLP-1 Therapy in Obesity Care: Continuation & Access Gaps.




