

Hair loss can look deceptively simple from the outside. A patient notices more hair in the shower, a widening part, a receding hairline or a visible patch, and wants to know which treatment will bring it back. But hair loss treatment rarely starts with choosing a product.
Similar-looking changes can come from very different processes. Pattern hair loss, telogen effluvium, alopecia areata and scarring alopecia differ in course, treatment goal and sometimes urgency, and a treatment appropriate for one may do little for another. That makes the first clinical question more important than the first prescription: what type of hair loss are we treating?
To understand how dermatology clinicians approach that decision, MDForLives surveyed dermatology professionals across the USA, Italy, France and Germany. The detailed findings are available in the MDForLives Hair Loss Management in Dermatology: Diagnosis, Treatment and Adherence Challenges Insight Report.
A familiar pattern should guide the assessment, not shortcut it
Some hair loss types are encountered far more often than others. In the MDForLives research, 65.4% of dermatology clinicians said androgenetic alopecia most often drives their evaluation, an understandable starting point, but familiarity should not become a shortcut.
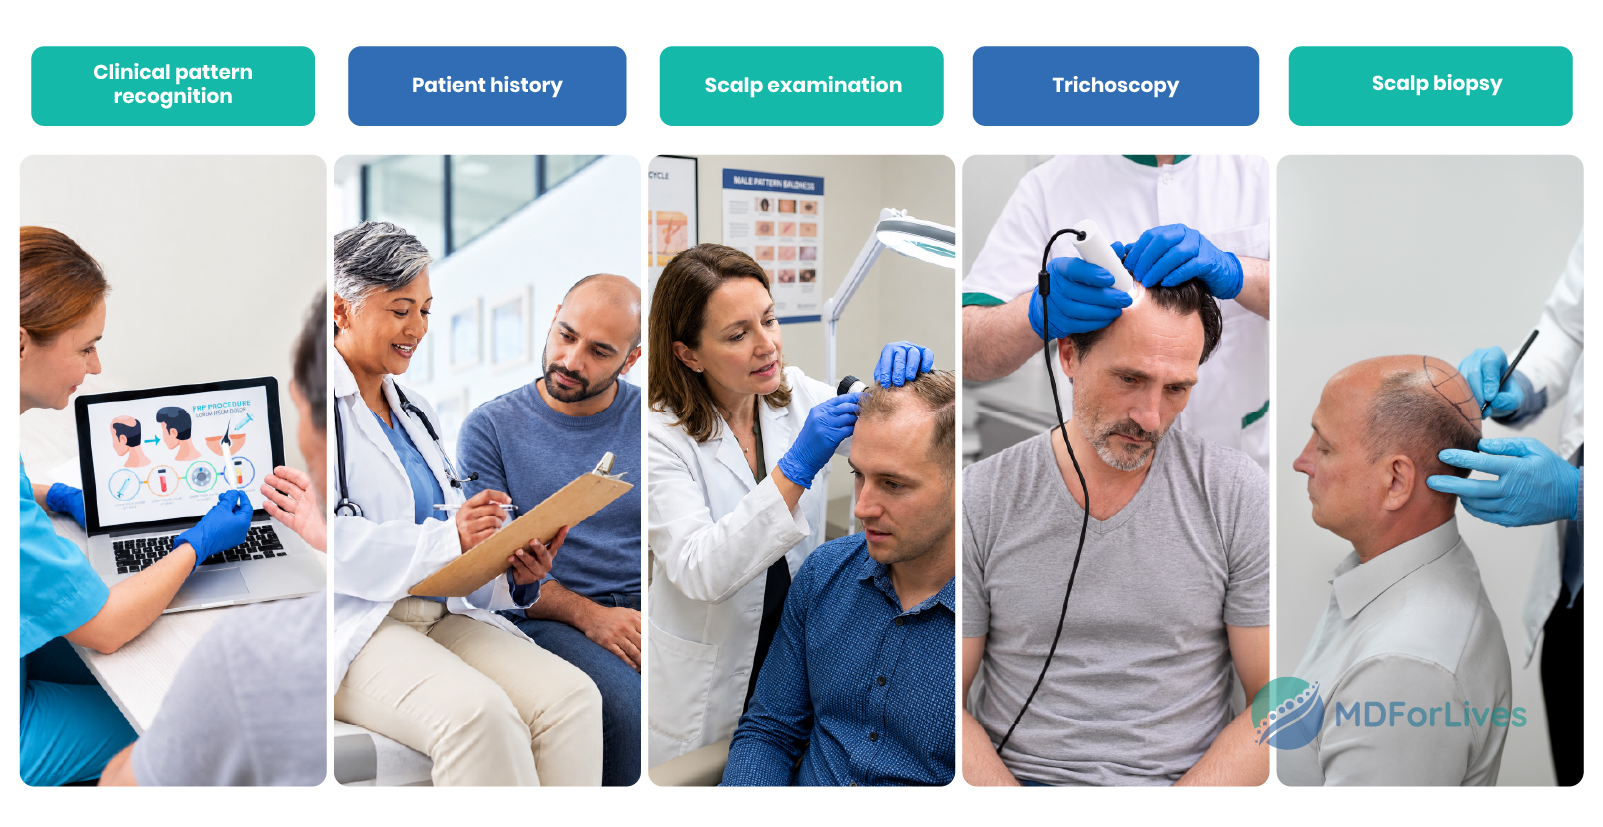
Diffuse shedding may coexist with pattern thinning; alopecia areata may not present as a classic patch, and early scarring disease can be subtle before follicular loss is obvious. A good hair loss diagnosis starts with pattern recognition but also weighs history, distribution, duration, shedding, scalp findings, symptoms, and medications.
Visible changes in the skin can sometimes provide clues about broader health concerns. Explore how skin signals may reflect underlying metabolic changes.
When the pattern is unclear, the workup needs to go deeper
Visual examination establishes a likely diagnosis in many patients; others need more evidence before treatment is selected or intensified. In the survey, 54.9% of clinicians selected trichoscopy abnormalities among the findings most likely to change their workup, while 47.1% selected scalp biopsy findings.
The implication is not that every patient requires advanced investigation, but that clinicians need clear points at which pattern recognition is no longer enough. Trichoscopy can reveal follicular and scalp features hard to appreciate on routine examination, and biopsy matters more when the diagnosis is uncertain, clinical and trichoscopic findings do not align, or scarring alopecia is suspected. This can prevent months of hair thinning treatment aimed at the wrong process; testing is most useful when it can change the pathway.
A visible skin concern does not always reveal its underlying cause. Understand the role and limitations of photographs in online dermatology consultations and skin diagnosis.
The most familiar treatment is not right for every diagnosis
Once the diagnosis is clearer, hair loss treatment options are easier to judge. Topical minoxidil was the most selected initial therapy, reflecting its role in pattern hair loss, but a common treatment should not become a universal answer to every thinning.
Different diagnoses require different goals. In androgenetic alopecia, slowing progression and maintaining density; in alopecia areata, treatment by severity and extent; in scarring alopecia, controlling inflammatory activity and preserving remaining follicles rather than simply stimulating regrowth. The sequence is simple: identify the process first, then choose the treatment that matches it. Starting with the therapy and working backward risks treating appearance rather than disease.
Slow improvement can make an appropriate treatment look ineffective
Even when the diagnosis and treatment are appropriate, hair-loss care faces another challenge, time: hair biology moves more slowly than patients would like. In the MDForLives survey, 49.0% of clinicians identified poor treatment adherence as the most common driver of initial treatment failure, with insufficient duration from another contributor.
Neither necessarily means the therapy has failed. A patient may stop because improvement seems too slow; treatment becomes inconvenient or continued shedding raises concern about the condition is worsening, so an appropriate hair loss treatment can look ineffective before a fair trial. This makes expectation-setting part of treatment, so slow biology is not mistaken for failure.
Persistent hair loss should trigger reassessment, not automatic escalation
When hair loss continues, the MDForLives research shows that pharmacotherapy escalation was the most commonly selected next step, while another group returned to diagnostic assessment, including scalp biopsy.
That split matters because “not improving” can mean different things. The therapy may need more time, adherence may have lapsed, disease activity may be progressing, or the diagnosis may no longer explain the course. Before escalation, two questions help: has the treatment had an adequate trial, and does the diagnosis still fit? The second matters most, because escalating without revisiting it can mean treating the wrong process more aggressively.
Scarring alopecia changes the urgency of getting the diagnosis right
Not all diagnostic uncertainty carries the same consequence. In the MDForLives research, 54.9% of clinicians identified active scarring alopecia as the subgroup most likely to change their treatment pathway, because scarring disease can change the objective itself.
In nonscarring alopecia, follicles remain, and regrowth may be possible; in scarring alopecia, follicular destruction can cause permanent loss. The question shifts from “how do we regrow more hair?” to “how do we control active disease and preserve the follicles that remain?” Delayed diagnosis may then mean losing time when progression could have been limited.
Expectations can determine whether a good treatment receives a fair chance
The right diagnosis and therapy still need realistic expectations. In the survey, 62.7% of clinicians identified unrealistic treatment expectations as the biggest limitation to effective hair-loss management. Hair-loss care is especially vulnerable because patients inspect their hair daily while meaningful change may take months.
Success does not always mean dramatic regrowth: depending on the diagnosis, reduced shedding, stabilized disease activity, preserved density or gradual improvement may all be meaningful. A useful conversation defines what success may look like, how long it may take, and when to reassess. An expectation gap can otherwise become an adherence gap.
Closing perspective: diagnose first, then judge the treatment
The question behind hair loss treatment is not which therapy works best, but whether it matches the process causing the loss. Pattern recognition may begin the assessment; trichoscopy or biopsy may clarify uncertainty, and treatment then needs time and adherence to be judged fairly. When loss continues, clinicians decide whether to escalate or reopen the diagnosis, more urgently with scarring disease.
The practical principle is straightforward: define the type of hair loss, match treatment to it, set realistic expectations and reassess when the course no longer fits. The right treatment starts with knowing what is being treated.




